
 Message us

Heart Stent Complete Guide: Which Stent Is Best?
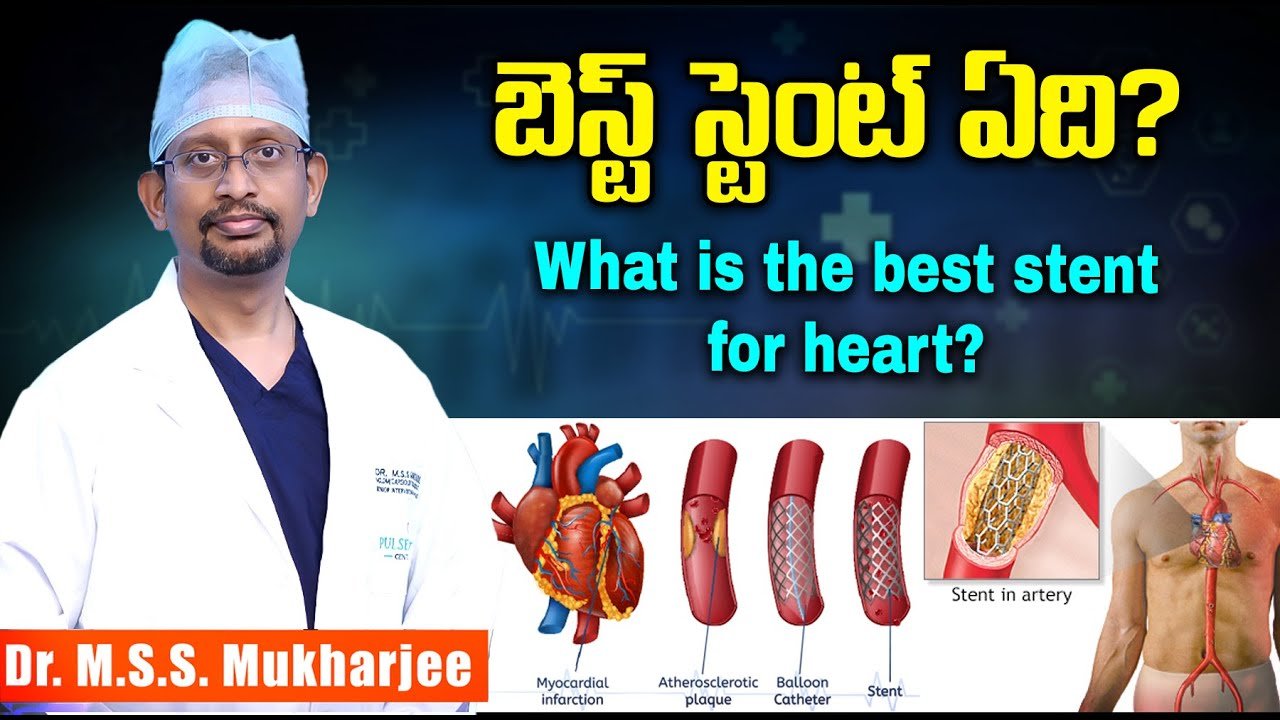
Today there is a very important thing we need to know. When a heart attack comes, stents are placed. At that time there is not much time even to think, and there are many doubts about which stent to put and what kind. It is a costly matter. When a heart attack comes, if a stent is not placed immediately, the patient's chance of survival is lower, so doctors tell you to decide on the stent quickly. That is correct. When a heart attack comes, the sooner we get the stent, the sooner the danger to life passes.
But in the little time available, what stents are good? What is the difference between old stents and new stents? How is a stent placed? Can blockages come again after a stent? What is stent thrombosis? Let us learn all these things. After seeing how many types of stents there are, we will also talk about the companies: which companies there are, which company's stent is good, and whether to get an Indian stent or a foreign stent.
Types of stents
Bare-metal stents
These are the old type: just metal mesh tubing, with no medicine, no drug coating. So after the stent was placed, over some time tissue grew around it and blockage could come again. The chance of blockage like that is 20 to 30%.
Medicated (drug-eluting) stents
Then came medicated stents, and now we use mostly medicated stents. They have medicine on them, which stops re-blockage. The medicine is around the stent and is released slowly. Because of this, the risk of restenosis, re-blockage, has come down a lot, to only about 7 to 10%. These are the stents we use most now.
Among drug-eluting stents there are first-generation, second-generation and third-generation stents. First-generation stents were a little thicker; gradually they are becoming thinner, and stent thickness is reducing. Not only that, the medicine on the stent is also changing: first it was paclitaxel, then sirolimus, and now everolimus-eluting stents are mostly used; there is zotarolimus too. You do not need to remember all these; at the end I will tell you how to decide which stent to use. Because of this medicine, tissue growth reduces, so the re-blockage chance falls to only 5 to 10%.
Biodegradable stents
An even newer type is biodegradable stents. About 10 years ago we placed biodegradable stents a lot, but they failed, because after use, clots inside them and re-blocks were higher, so they were withdrawn. Biodegradable stents may come again in future, available after some years. Their advantage is that the stent does not stay in the body, so the blood vessel stays natural and can slowly get better, and pumping can also get better.
How a stent is placed
Placing a stent, as you know, is not like open-heart surgery. It is a minimal-access procedure, done either through the hand or through the leg. First we give a little local anaesthesia, through the leg, meaning the thigh, or through the hand, meaning the wrist.
- From here we introduce a small catheter and place it at the beginning of the heart's blood vessel. This is called the guiding catheter.
- From there we pass a small wire down. This wire, as thin as a hair, lets us send a balloon or stent over it. If we simply pushed without it, the blood vessel could get damaged here and there. This is called the guide wire.
- To see where the blockage is, we do an angiogram: when an injection is given, everything becomes visible, which is not normally seen on X-ray. Where it looks narrow, there is a blockage.
- Where there is a blockage, we inflate a balloon there and widen the blood vessel. After the balloon is removed, it would close again.
- To stop it closing, we introduce the stent.
Wrist (radial) or groin (femoral)?
The radial access, done through the hand, has less bleeding and the patient recovers quickly; they can get up and walk immediately. Femoral access, through the large blood vessels of the leg, is used when we need a slightly larger catheter. Catheter sizes are 6 French, 7 French and so on. Up to 6 French can be done from the hand; at 7 French and above we do it from the leg.
Restenosis: blockage again after a stent
If blockage comes after a stent, it is called restenosis. Usually it can come within one year; usually it does not come after a year. In the old bare-metal stents it was a little higher. Now, with second- and third-generation medicated stents, re-block chances have reduced.
But because re-block rates are lower, we now place stents in more complex cases. At a bifurcation, a Y junction where one blood vessel branches into two, re-block chances are higher. If the stent is very long, re-block chances are higher. If the vessel is thin and the stent is small, re-block chances are higher. And if we expand the stent well, re-block chances are lower; if not, they are higher.
If restenosis comes, sometimes medicines alone are enough. Sometimes we do angioplasty again, placing another stent there, or using a medicated balloon. Sometimes bypass surgery is done. With these we can treat restenosis.
Stent thrombosis: a clot inside the stent
These two are the main problems with stents: restenosis and stent thrombosis. Restenosis, re-blocking, does not happen immediately; it happens after six to nine months. Stent thrombosis can happen immediately. The risk continues up to the first year, but it is highest in the first 48 hours. Blood clots form inside the stent and it gets blocked.
If it happens right then, it is called acute; after days or weeks, subacute; after many months or a year, late stent thrombosis.
Why does it come? If medicines are not taken properly: the aspirin, clopidogrel, ticagrelor and similar medicines we give. If they are not taken properly, it can come. In some people they do not work properly, and then too it can come. If sugar is not controlled or BP is high, it can come. If the stent is not deployed properly, a clot can come immediately, on the table itself.
If it comes, heart attack risk is very high. Stent thrombosis should be considered the same as a heart attack. If we do not treat it immediately, there is danger to life. So if there is stent thrombosis, treatment is needed immediately. That is how careful we need to be.
Since stent thrombosis is a dangerous problem, what should we do? Take the antiplatelet medicines correctly, keep BP and sugar carefully under control, and give up drinking and smoking. The first year after a stent is very crucial, so be very careful.
Precautions you must follow after a stent
- Take medicines every day at the right time. Very, very important.
- Walk for some time and exercise.
- Reduce foods with a lot of fat and oil.
- Give up smoking completely.
- Get tested regularly, because sometimes we think we are taking the medicines but there are some differences; when checked regularly, the cardiologist can advise on the medicines again.
Which company's stent?
Very important: which company's stent to get. There are mainly foreign stents and Indian stents.
Among foreign stents there are three companies. At Pulse we use two, which is why I am showing you these two. One is the Abbott company stent, Xience, one of the leading stents in the whole world now. Second is Boston Scientific, with Promus and Synergy; these stents are also among the most used in the world. Along with these there is a company called Medtronic; we are not using it now, we use these two, but Medtronic is also a good company. So these three companies, Abbott, Boston Scientific and Medtronic, make the stents placed in all major hospitals in the world.
Indian stents are also good. To compare, these foreign stents usually have US FDA approval, so it is better to use stents with US FDA approval. Among Indian stents there is a company called SMT, and another called Yukon Choice. They can also be used.
If anyone is placing stents from these three companies, you can get them without hesitation; there is no need to think much about it. So if you ever want foreign stents, look for these three: Abbott, Boston Scientific, Medtronic. If you want an Indian company, there are two main ones: SMT stents and Yukon stents. Both are relatively well-known stents in India.
A real case: emergency angioplasty
Let us look at the angioplasty of a patient we did this Sunday. She is a 35-year-old lady. A heart attack at this age is very rare in ladies. In men it comes quite a lot, especially in smokers even at this age, but in ladies it is very, very rare.
Her right-side blood vessel was very small, and only her two left-side vessels were large. The vessel coming from below was fine all the way. But in the vessel coming from above, from here it turned white: a clot. Because of this clot, blood supply was not going down.
There were several problems in doing her angioplasty in this emergency. First, there was clot at the junction between the two vessels too, so the clot could come into the other branch. If it did, since her right-side vessel was very small and only the two left vessels were large, if this one also closed, death could occur on the table itself. That is how major the problem was. Second, the stent we place could also block the other branch, so the stent had to be placed carefully. Third, at such a junction we need a 7 French catheter, which we usually do from the leg, but I did it from the hand because she is a little obese, and from the leg the bleeding risk would be higher.
First we passed a wire inside. Then a thrombus suction catheter, an instrument that pulls out the clot. We pulled the clot two or three times. Meanwhile her BP was not being maintained; it was around 60 to 70, and she had very severe chest pain. We had to do this work while maintaining her BP.
After pulling the clot, it reduced a little here, but it moved into the other branch, exactly what we feared. Now there was danger of this branch closing too, an immediate danger to life, and the BP had already begun falling further. There are clot-dissolving injections; we gave tirofiban, and the clot dissolved there. Some clot cleared and went down.
Then we came back to the main vessel. Blood supply was not reaching down, so we placed the wire there and began pulling the clot again. After it got somewhat better, we took the stent. Where to place it? If placed from here to here, it would block the other branch, so I decided to start exactly here: nailing it precisely. Even one millimetre of difference, even her breathing, makes a difference; one millimetre back and it would come into the main vessel. We adjusted it back until it was exactly at the beginning, covering completely without compromising the other branch. Then the stent was expanded.
After expanding it, we placed another balloon inside the stent. It was a 3 mm × 18 mm stent, so inside it we put a 3.25 × 15 mm balloon at very high pressure, up to 26 atmospheres. Now everything was clear and blood supply was going down clearly. Earlier everything was white and blood was not going properly; now it flows clearly.
After this, her pain went away immediately. We did it on Sunday and today we are discharging her. She is comfortable. But it was a big problem for her: her heart pumping has become very weak, and she must be careful for a year. However well we place a stent, there are two stent-related risks: re-block in the stent and a clot in the stent. A clot in the stent is rare but dangerous, so to prevent it she must take the tablets carefully, change her lifestyle, reduce some weight and keep cholesterol under control.
If you need a stent in an emergency
If you have a heart attack and need a stent, say okay immediately. As for stent companies, any of Abbott, Boston Scientific or Medtronic is fine, and Indian stents are also fine. If those three are not there, getting whatever stent is available there is what matters. But if available, request one of these three. After a stent, careful monitoring and changing your lifestyle are very necessary.
In his words: the key point
In a heart attack, agree to the stent immediately. Abbott, Boston Scientific or Medtronic are good, Indian stents (SMT, Yukon) are also fine, and if none are available, whatever stent is there is what matters. Take the medicines carefully; the first year is crucial.
Frequently asked questions
Which stent is best?
Dr. Mukharjee says stents from Abbott (Xience), Boston Scientific (Promus, Synergy) and Medtronic, which have US FDA approval, can be taken without hesitation; Indian stents from SMT and Yukon are also good. At Pulse Heart, Abbott and Boston Scientific stents are used.
Can an artery block again after a stent?
Yes. With modern medicated stents the re-block chance is about 5 to 10%, usually within a year, and more likely with long stents, small vessels, bifurcations or an under-expanded stent.
What is stent thrombosis?
A clot inside the stent, most likely in the first 48 hours and up to a year. It should be treated like a heart attack. Taking aspirin, clopidogrel or ticagrelor properly and controlling sugar and BP prevent it.
Is angioplasty done through the hand or the leg?
Usually through the wrist, with less bleeding and faster recovery. Up to 6 French catheters can be used from the hand; 7 French and above are usually done from the leg.
— Dr. M. S. S. Mukharjee
Senior Interventional Cardiologist
Pulse Heart Super Speciality Hospital, Miyapur, Hyderabad
This article is for educational purposes only and isn't a substitute for individualised medical advice. Talk to your own doctor before starting, stopping or changing any medicine.